When it may be considered
Pelvic exenteration may be considered for selected cancers that involve neighbouring pelvic organs or recur after previous treatment. These include some rectal cancers and tumours arising in other pelvic organs. It is not appropriate for every advanced cancer. Disease distribution, prior treatment and physical fitness determine whether a meaningful resection is feasible and what the operation is intended to achieve.
Specialist multidisciplinary assessment
Assessment combines pathology, detailed pelvic imaging and evaluation for distant disease. Previous surgical and radiotherapy records matter. Colorectal, urological, gynaecological and reconstructive specialists may contribute. Nutrition, cardiopulmonary fitness, kidney function and independence are reviewed. Treatment goals and support at home should be discussed, because technical feasibility alone does not establish an acceptable balance of benefit and burden.
Alternatives and treatment goals
Alternatives may include systemic treatment, selected radiotherapy or reirradiation, more limited procedures and symptom-focused care. Available options depend on previous treatment and tumour biology. The intended goal of exenteration should be explicit. Pain and symptom management remain important regardless of the choice. A second specialist opinion can help, while personal priorities and lasting functional changes deserve balanced discussion.
Which organs may be involved?
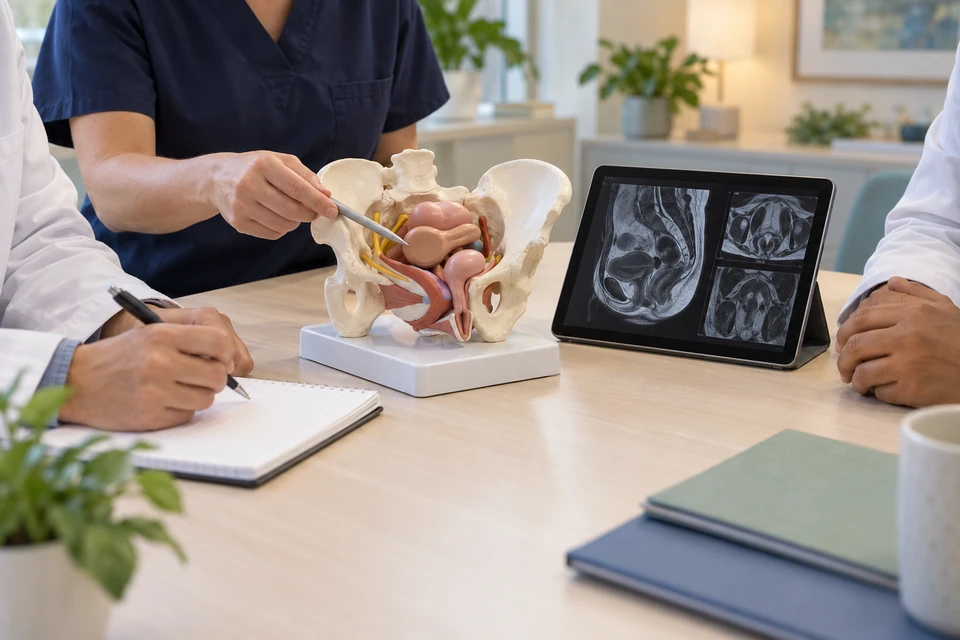
The extent varies: surgery may remove the rectum, bladder or reproductive organs in different combinations. Some cases need additional work on surrounding muscles, vessels or bone. A bowel stoma and a separate urinary diversion may be required. Tissue reconstruction can help close the resulting defect. Not every patient has the same organs removed, so proposed reconstructions and lasting changes need individual explanation.
Risks and lasting effects
Risks include major bleeding, severe infection, clots, wound-healing difficulties and further operations. Bowel or urinary leakage, impaired kidney function and nutritional problems may occur. Sexual function, fertility, body image and mobility can change permanently. Previous radiotherapy or surgery can complicate healing. The discussion should include prolonged rehabilitation and support needs as well as immediate surgical risk.
Preparation and rehabilitation
Preparation includes nutritional and physical conditioning, psychological support and practical planning at home. Stoma and urinary-diversion education may begin before surgery. Recovery can require intensive monitoring, followed by gradual mobilisation and nutritional support. Wounds, output and kidney function need review. Supplies and caregiver support should be arranged before discharge. Follow-up combines cancer assessment with physical rehabilitation and emotional adjustment.
Urgent warning signs during recovery
Fever, shivering, increasing pelvic or abdominal pain, offensive wound discharge or sudden deterioration need prompt assessment. Report reduced urine, unexpected stoma changes or persistent vomiting immediately. Chest pain, breathlessness, heavy bleeding or fainting may require emergency care. Because several reconstructions may need attention, discharge instructions should provide clear contact pathways. Tell any new healthcare team exactly which operations and diversions were performed.
This information is general. The cause of symptoms, appropriate investigations and treatment options are determined through individual assessment.