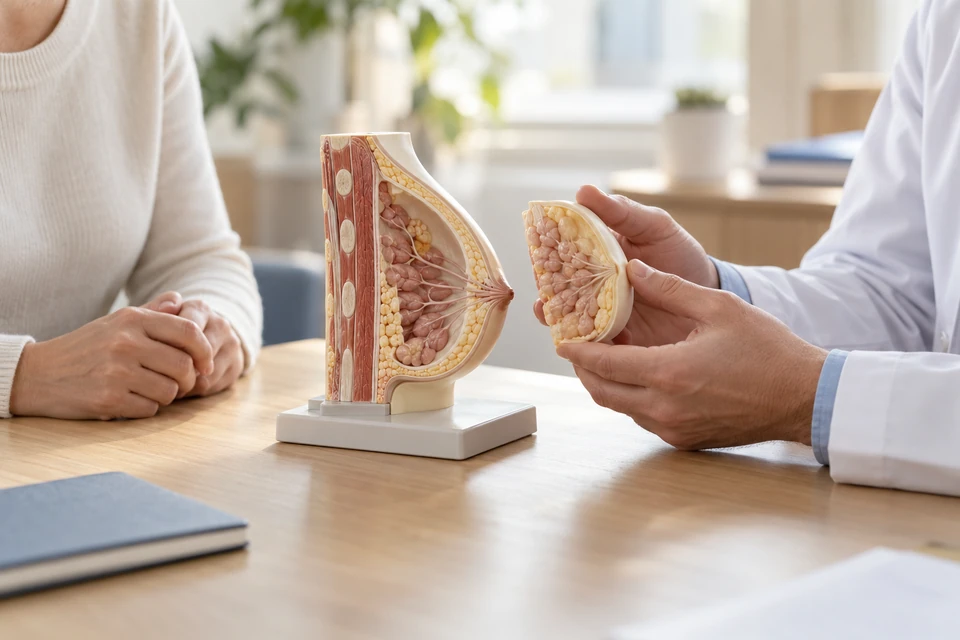
When may mastectomy be recommended?
Mastectomy may be considered when disease is too extensive for suitable conservation, clear margins cannot be achieved, or other factors limit breast-preserving treatment. Some patients choose it after comparing options. Risk-reducing surgery for inherited susceptibility is a separate decision requiring appropriate assessment rather than being a routine response to any cancer diagnosis.
Different extents of surgery
Removing the breast does not automatically require removing all axillary nodes. Simple mastectomy and operations incorporating axillary dissection are different. Skin- or nipple-sparing approaches are possible in selected cases, depending on cancer location and tissue viability. The proposed operation should clearly identify what will be removed and what may be preserved.
Assessment for surgical planning
Planning reviews biopsy results, imaging and axillary findings. Genetic counselling or preoperative systemic treatment may be relevant. Reconstruction requires additional assessment of medical conditions, smoking, previous surgery and likely radiotherapy. Eligibility for implants or tissue-based reconstruction cannot be determined from photographs or another person's experience alone.
Reconstruction or flat closure
Reconstruction may be immediate or delayed and can involve implants or your own tissue. A planned flat closure is also a valid option. Each choice has different implications for healing, sensation and further surgery. Likely radiotherapy can influence the recommendation, so cancer treatment and personal priorities should be discussed together.
The operation and pathology
The operation is performed under general anaesthesia according to the agreed plan. A lymph-node procedure and temporary drains may be needed. Pathology provides further information about disease extent and margins. Mastectomy does not necessarily remove the need for radiotherapy or systemic treatment, and the final results must be discussed.
Risks and lasting effects
Potential complications include bleeding, infection, fluid collection, delayed healing and reduced skin viability. Numbness, tightness or persistent pain can occur. Reconstruction and axillary dissection add separate risks. Changes in body image, clothing and intimacy are legitimate concerns, and support should be tailored to the individual's needs.
Preparation and care at home
Preparation includes medicine review, anaesthetic assessment and arrangements for help at home. Wound and drain care should be demonstrated. Shoulder movement and daily activity are tailored to the operation rather than governed by one universal restriction. Written instructions should identify contact details, follow-up appointments and the pathology discussion.
Follow-up and warning signs
Follow-up addresses healing, movement, drains and additional treatment. Any remaining breast continues appropriate screening, and new chest-wall lumps or skin changes should be reported. Fever, spreading redness, offensive discharge or rapidly increasing swelling need prompt review. Sudden breathlessness or chest pain requires emergency assessment.
This information is general. The cause of symptoms, appropriate investigations and treatment options are determined through individual assessment.