When is it considered?
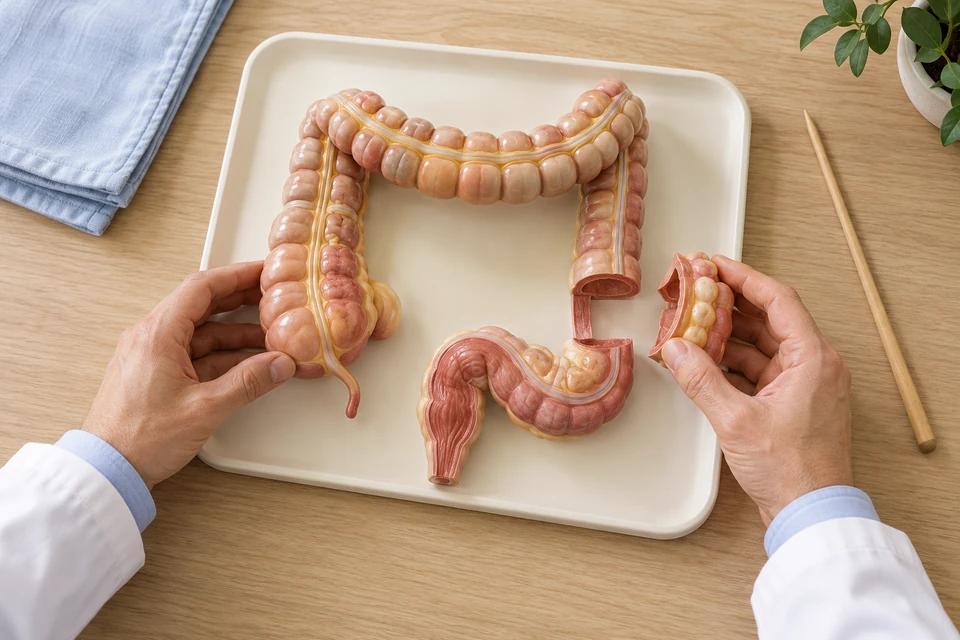
Colon resection is a general term for removing part of the large bowel, rather than a diagnosis. Reasons include cancer, selected polyps unsuitable for endoscopic removal, complicated diverticular disease, narrowing, impaired blood supply or injury. The goal may be tumour removal, relief of obstruction or infection control. Right or left hemicolectomy and sigmoid resection are different forms of this operation.
Diagnosis and extent
Assessment establishes where the disease is and how much bowel is affected. Colonoscopy, biopsy, CT and blood tests are chosen according to the suspected cause. Cancer operations usually include regional lymph nodes; benign disease may need a different extent. Previous operations, nutrition, kidney function and usual bowel habits matter. In an emergency, infection or obstruction may need treatment before a full elective work-up is possible.
Considering alternatives
Some conditions can be managed without resection. Suitable polyps may be removed endoscopically, inflammatory disease may respond to medicines and certain abscesses can be drained. These options are not interchangeable with cancer surgery. The team compares the consequences of waiting with operative risks. Establishing whether the identified bowel problem actually explains the symptoms helps avoid assuming surgery will resolve every abdominal complaint.
How the operation proceeds
The diseased segment and necessary surrounding tissue are removed. If blood supply and local conditions are suitable, the remaining ends are joined in an anastomosis. A temporary or permanent stoma may be safer in other circumstances. Surgery can be open or minimally invasive, with conversion when necessary. The specimen is examined by pathology, which can refine the diagnosis and subsequent treatment.
Risks and functional changes
Important risks include a leaking connection, infection, bleeding, temporary bowel inactivity and later obstruction from adhesions. Injury to nearby structures, an incisional hernia, blood clots and anaesthetic complications are also considered. Stool frequency or consistency can change according to the segment removed. Individual risk reflects overall fitness, nutrition, other conditions and whether the operation is planned or urgent.
Preparation, nutrition and follow-up
Preparation addresses anaemia, nutritional deficits, smoking and suitable physical activity. Follow individual instructions for fasting, bowel preparation and medicines. After surgery, eating and movement increase according to progress. At home, monitor bowel changes, fluid intake and the wound. Recovery restrictions should reflect the operation and your condition. A pathology review is essential, and cancer may require additional treatment and ongoing surveillance.
Warning signs during recovery
Worsening abdominal pain, fever, persistent vomiting, marked swelling or a decline in general wellbeing require prompt advice. Reduced bowel output is more concerning when accompanied by pain or vomiting. Wound opening, spreading redness or offensive discharge also need assessment. Heavy bleeding, fainting, chest pain or breathlessness warrant emergency care. A rapidly deteriorating pattern should not be dismissed as ordinary recovery.
This information is general. The cause of symptoms, appropriate investigations and treatment options are determined through individual assessment.